

- If you got worse on treatment, that was information. It usually means things were dying faster than your body could clear what they released.
- Drainage before killing. Liver, bile, lymph, bowel and kidney have to be moving before you mobilise anything, or the toxins recirculate.
- A Herxheimer reaction is not the therapy failing — it usually means it is working. But it is far more comfortable when it is anticipated and managed.
- Mold illness and Lyme frequently occur together, and treating one while ignoring the other is why so many protocols stall.
- This is a long game. Anyone promising a fast resolution has not treated many of these patients.
Why you got worse the moment treatment started
This is the single most common story we hear, and it is the reason so many people conclude that nothing works for them.
When you kill an organism, it does not simply vanish. Bacterial cell walls release endotoxins. Fungal organisms release mycotoxins. Cell debris enters circulation. Your immune system responds to all of it.
That response is a Herxheimer reaction — flu-like aching, fatigue, headache, sometimes a low fever, occasionally a genuine worsening of every symptom you had. It typically appears within a day or two of starting or escalating treatment.
Here is what patients almost never get told: this is usually a sign the treatment is working. It is not an allergy and it is not a failure. But it is also not something you should simply endure, because the intensity of it depends almost entirely on whether your body can clear what has been released — and that is something we can prepare in advance.
Which is the entire argument for sequence. Open the exits first, then start killing.
What drainage actually means
Patients hear the word constantly in this world and rarely get a straight explanation of it. Drainage means the physical routes by which your body removes waste, and there are five that matter.
The bowel. The final exit. If you are not having at least one full bowel movement a day, toxins conjugated by the liver and dumped into bile get reabsorbed rather than leaving. This is the first thing we address and the least glamorous.
Bile flow. The liver packages fat-soluble toxins into bile. If bile is thick or sluggish, that packaging sits in the gallbladder rather than moving out. Bitters, taurine, phosphatidylcholine and adequate hydration all matter here.
The liver itself. Phase one converts toxins into intermediates, phase two makes them water-soluble enough to leave. Phase two requires glutathione, sulphur, glycine and B vitamins — and if phase one is running faster than phase two, you accumulate intermediates that are often more reactive than what you started with.
The lymphatic system. It has no pump. It moves through muscle contraction, breathing and vessel dilation, which is why movement, rebounding, sauna and dry brushing are genuine interventions rather than wellness theatre.
The kidneys. Water-soluble waste leaves here, and adequate hydration is the whole story.
We assess all five before we start, and we do not begin antimicrobial work until they are moving.
The five exits, and the order of treatment
Almost every failed protocol we see failed on sequence rather than on ingredients. The order above is the treatment.
The testing that finds it
One point on the building itself. If mold is the driver and you are still living or working in the environment that caused it, no protocol will get ahead of the exposure. That assessment comes before treatment, not after.
The ten levers in chronic infection care
In the order we actually use them. The sequence is the treatment.
Open Drainage First
Bowel, bile, liver, lymph and kidney — assessed and moving before anything antimicrobial begins. This single decision determines whether the following months are tolerable or miserable, and it is the step most protocols skip.
What the evidence showsMobilising toxins before hepatic, biliary, renal and lymphatic clearance routes are functioning results in redistribution rather than elimination — the mechanistic basis for staging drainage before any antimicrobial or binding agent.Remove the Ongoing Exposure
If mold is the driver and the building has not been addressed, you are treating into a headwind. This is uncomfortable and expensive and it is not optional — it is the difference between recovery and a permanent protocol.
What the evidence showsBorrelia can persist in biofilm communities that substantially reduce antimicrobial penetration, and biofilm-disrupting agents are used to improve access to organisms within that matrix.Bind What Is Released
Binders — activated charcoal, chlorella, bentonite, cholestyramine where prescribed — capture mobilised toxins in the gut so they leave rather than recirculating. Timing matters, away from food and other supplements.
What the evidence showsMycotoxins including ochratoxin A and trichothecenes are measurable in urine and have documented immunosuppressive and inflammatory effects at environmental exposure levels.Correct Nutrient Depletion
Years of chronic illness deplete iron, B12, vitamin D, magnesium and zinc, and every one of those is required for immune function and detoxification. Correcting them often produces the first genuine improvement patients have felt in years.
What the evidence showsIn genetically susceptible individuals, HLA haplotypes affecting antigen presentation are associated with impaired biotoxin clearance and persistent inflammatory response after exposure ends.Support the Terrain Before Killing
A body that cannot mount a proper immune response will not clear an infection regardless of what you throw at it. Sleep, blood sugar, protein and stress physiology are the foundation, and skipping them is why protocols stall.
What the evidence showsBile is a primary excretion route for fat-soluble biotoxins, and binding agents including cholestyramine and activated charcoal interrupt enterohepatic recirculation.Then Address the Organisms
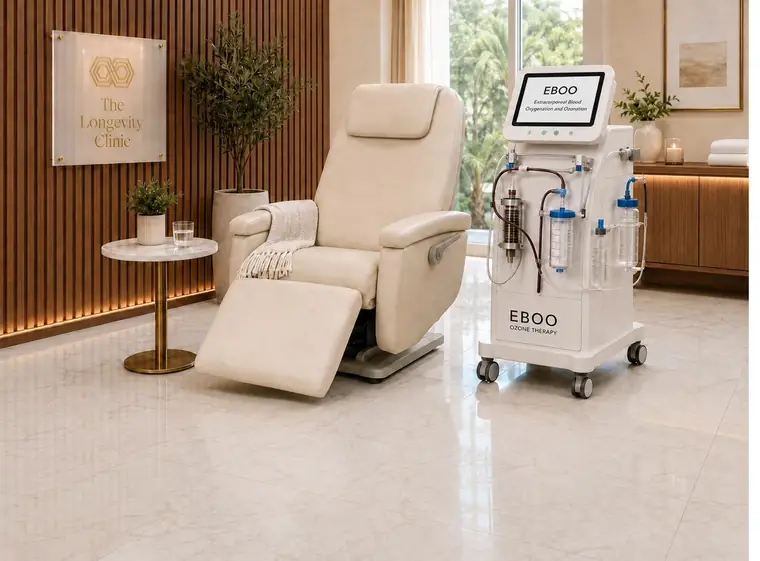
Herbal antimicrobials, prescription antimicrobials where appropriate, and ozone therapies. Started low and escalated slowly, because the speed of killing determines the severity of the reaction.
What the evidence showsOzone is directly active against anaerobic organisms and modulates immune signalling. EBOO adds physical filtration of inflammatory mediators, distinct from ozonation alone.Use Ozone Therapy Strategically
Ozone is directly hostile to anaerobic organisms, and many of the pathogens here are built for low-oxygen environments. EBOO adds filtration, physically removing material rather than only treating it. Always after drainage, never before.
What the evidence showsChronic infection depletes nutrient reserves through increased demand and impaired absorption, and deficiency in zinc, vitamin D and B vitamins independently impairs immune competence.Add Hyperbaric Oxygen
Raising tissue oxygen tension is unfriendly to the organisms involved and supports the repair the body has been unable to do. Particularly useful where neurological symptoms dominate.
What the evidence showsHerxheimer reactions result from endotoxin and cell debris release exceeding clearance capacity. Starting at reduced intensity with drainage established measurably reduces reaction severity.Address Mast Cell Activation
A significant share of these patients develop mast cell activation alongside, which produces the sensitivity to foods, smells and supplements that makes every protocol difficult. Recognising it changes the approach entirely.
What the evidence showsMast cell activation frequently accompanies chronic infection and biotoxin illness, and stabilising mast cells before aggressive treatment reduces the inflammatory response to die-off.Rebuild, Do Not Just Kill
The end of treatment is not the end of care. Mitochondrial support, gut repair and nervous system regulation are what turn a cleared infection into a recovered person, and this phase is routinely skipped.
What the evidence showsRemediating ongoing environmental exposure is a prerequisite for recovery in mold illness, as continued exposure reintroduces the burden faster than treatment can clear it.What patients commonly experience under our care
When patients receive the proper guidance, here is what they commonly experience under our care.
- Weeks 1–3 — drainage phase. Before anything antimicrobial. Patients frequently notice improvement here alone — better bowel regularity, less headache, clearer thinking — because reduced toxin recirculation lowers the load on its own.
- Weeks 4–8 — the treatment phase. This is where die-off reactions occur, and with drainage open and a slow escalation most patients move through it comfortably rather than losing weeks. Symptoms often fluctuate before they improve.
- Months 3–6 — the corner. hs-CRP falling. Mycotoxin levels dropping on repeat testing. Ferritin and B12 normalising. Patients typically describe a corner being turned here — more good days than bad for the first time in years.
- Months 6–12 — rebuilding. Energy, cognitive endurance and exercise tolerance returning. This is the phase most protocols skip and the one that determines whether someone stays well after treatment ends.
If you have been dismissed, told your tests are normal, or felt worse every time you tried to get better, please do not conclude that this is simply how you are now. Schedule a consultation and let my team sequence this properly, starting with drainage. We will not stop until the root cause of every one of your health issues has been found and addressed.
Drainage assessed and opened first, testing that actually finds what is there, and a protocol escalated at a pace your body can handle.
Common questions
Why do I feel worse when I start treatment for Lyme or mold?
That is a Herxheimer reaction — organisms dying faster than your body can clear what they release. Endotoxins and cell debris enter circulation and your immune system responds, producing flu-like aching, fatigue and headache for a day or two. It usually means the treatment is working, but the severity depends almost entirely on whether your drainage pathways are open, which is why we address those first.
What does drainage mean in functional medicine?
The physical routes by which your body removes waste: the bowel, bile flow, the liver's detoxification pathways, the lymphatic system and the kidneys. If any of those are sluggish, mobilised toxins recirculate rather than leaving. We assess and open all five before beginning antimicrobial treatment.
Is there a Lyme literate doctor near Nashville?
We treat chronic infection, Lyme and co-infections, and mold illness at our clinic in Franklin, Tennessee, about twenty minutes south of downtown Nashville. We run comprehensive tick-borne panels alongside mycotoxin testing, viral titres and inflammatory markers, and we sequence treatment drainage-first.
How do you test for mold illness?
Urinary mycotoxin testing measures what your body is actually carrying and clearing. We run it alongside inflammatory markers including C4a and TGF-beta where the picture fits, plus a full nutrient panel. Testing the building itself matters equally — if the exposure is ongoing, no protocol gets ahead of it.
How long does treatment take?
Longer than anyone wants to hear. Drainage takes two to four weeks. Antimicrobial work typically runs three to six months. Rebuilding runs six to twelve. Anyone promising resolution in weeks has not treated many of these patients, and the rebuilding phase that most protocols skip is what determines whether you stay well afterwards.
- Shoemaker RC, House DE. Sick building syndrome and exposure to water-damaged buildings. Neurotoxicology and Teratology. 2006;28(5):573–588.
- Chedid V, et al. Herbal therapy is equivalent to rifaximin for the treatment of small intestinal bacterial overgrowth. Global Advances in Health and Medicine. 2014;3(3):16–24. PMC4030608
- Butler T. The Jarisch-Herxheimer reaction after antibiotic treatment of spirochetal infections. American Journal of Tropical Medicine and Hygiene. 2017;96(1):46–52. PMC5239707
- Hope J. A review of the mechanism of injury and treatment approaches for illness resulting from exposure to water-damaged buildings, mold, and mycotoxins. The Scientific World Journal. 2013.
- Bocci V. Ozone: A New Medical Drug. 2nd edition. Springer, 2011.
This article is educational and reflects the published literature as of August 2026. It is not a diagnosis or a treatment recommendation for any individual, and any decision about your care belongs in a conversation with a licensed practitioner who has seen your history and your labs.